Verified
The first week brought loose stools after breakfast. Taking the tablet with a full meal helped, and the symptoms became occasional by the third week. My morning readings improved gradually rather than immediately.
20 Oct 2026

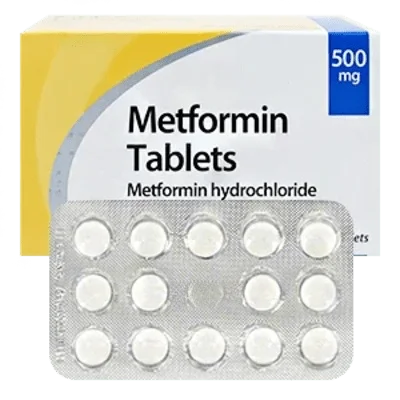
Metformin is an oral biguanide medicine for adults with Type 2 diabetes. It helps lower blood glucose by reducing glucose production in the liver and improving insulin sensitivity. Its benefits develop gradually as part of an ongoing diabetes care plan.
It is prescribed when the body does not use insulin efficiently or the liver releases too much glucose. Metformin lowers hepatic glucose production and improves insulin sensitivity without directly stimulating insulin release. Its effect develops gradually with regular use.
Metformin tablets contain metformin hydrochloride, an oral antidiabetic substance from the biguanide class. The dose is stated on the pack — follow the leaflet.
Metformin acts mainly on the liver. Its pharmacological effect reduces gluconeogenesis, the process through which the liver creates glucose from non-carbohydrate substances such as lactate, glycerol, and amino acids.
The medicine also influences cellular energy signalling. Research from Yale School of Medicine has described metformin’s effects on mitochondrial energy handling and pathways linked with AMP-activated protein kinase, or AMPK. AMPK functions as an energy sensor inside cells. When activated or influenced by changing cellular energy conditions, it can reduce energy-intensive glucose production and support better metabolic balance.
Muscle tissue may also respond more effectively to insulin during metformin treatment. This can increase glucose uptake after meals, although the result varies with physical activity, disease duration, body composition, and remaining pancreatic function.
The medicine has a different mechanism from insulin secretagogues. It does not increase insulin secretion directly, so metformin alone has a low risk of hypoglycaemia. The risk rises when it is combined with insulin or medicines that stimulate insulin release. The FDA prescribing information describes this distinction and the renal precautions associated with treatment [2].
Doctors use metformin as a foundational treatment for Type 2 diabetes, alongside nutrition, physical activity, weight management, and regular glucose monitoring.
The medicine may be used alone or combined with other glucose-lowering treatments. Its main purpose is to reduce elevated blood glucose and improve the body’s response to insulin. NICE guidance places metformin within the initial treatment pathway for many adults with Type 2 diabetes, with later treatment decisions based on glucose control, kidney function, cardiovascular risk, and other clinical factors [1].
Metformin can remain useful when Type 2 diabetes progresses and insulin injections become necessary. Insulin replaces or supplements the hormone that the pancreas can no longer provide in sufficient amounts. Metformin improves insulin sensitivity and reduces liver glucose output, while insulin moves glucose from the blood into tissues.
Combining the two approaches may help some patients achieve glucose targets with less insulin than would otherwise be required. The exact plan depends on glycated haemoglobin, fasting glucose, meal patterns, kidney function, body weight, and the person’s risk of hypoglycaemia.
| Treatment approach | Main pharmacological effect | Common clinical consideration |
|---|---|---|
| Metformin alone | Reduces liver glucose production and improves insulin sensitivity | Low hypoglycaemia risk when used without insulin-releasing medicines |
| Insulin alone | Directly increases glucose uptake and suppresses glucose production | Requires glucose monitoring and dose adjustment |
| Metformin plus insulin | Combines improved insulin sensitivity with direct hormone replacement | Hypoglycaemia risk comes mainly from insulin; weight change may require monitoring |
A person who starts insulin should not stop metformin independently. The two medicines may serve different purposes, and abrupt changes can destabilise glucose control.
GLP-1 receptor agonists, including semaglutide products such as Ozempic and Rybelsus, work through incretin biology. They enhance glucose-dependent insulin release, reduce glucagon secretion, slow gastric emptying to varying degrees, and may reduce appetite. Metformin works mainly through hepatic and insulin-sensitivity pathways.
The treatments can be used in the same diabetes plan when clinically appropriate. They are not interchangeable in route, monitoring needs, adverse effects, or treatment goals.
| Feature | Metformin | Semaglutide-based GLP-1 treatment |
|---|---|---|
| Administration | Oral tablet | Injection or oral tablet, depending on formulation |
| Main action | Reduces hepatic glucose production and improves insulin sensitivity | Activates GLP-1 receptors, increasing glucose-dependent insulin release and reducing glucagon |
| Weight and tolerability | Usually weight-neutral or associated with modest weight reduction; gastrointestinal effects are common early | Often produces greater weight reduction; nausea, vomiting, and reduced appetite may occur |
Semaglutide may be selected when additional glucose lowering, weight reduction, or cardiovascular risk reduction is clinically relevant. Metformin remains useful because it is oral, familiar in practice, and mechanistically different. Gastrointestinal intolerance can limit either treatment, especially when doses rise quickly.
Ozempic contains semaglutide and is administered by injection. Rybelsus contains semaglutide in an oral formulation, but its administration requirements differ from ordinary tablets because absorption is sensitive to food and fluid timing. A clinician chooses the treatment sequence according to the person’s medical profile rather than the medicine’s popularity.
Metformin may be unsuitable or require specialist adjustment in the following circumstances:
Alcohol can increase lactic acidosis risk, especially when intake is heavy or accompanied by poor nutrition, vomiting, or dehydration. Avoid binge drinking while using metformin.
Iodinated contrast procedures require advance planning. Depending on kidney function and the procedure, metformin may need to be paused and restarted only after renal function has been reassessed. Tell the imaging team that you use metformin before contrast administration.
Cimetidine and some medicines that affect kidney tubular secretion may increase metformin exposure. Corticosteroids, diuretics, beta-agonists, and some antipsychotic medicines can raise blood glucose and may alter diabetes control. Insulin and insulin-releasing medicines can increase hypoglycaemia risk when combined with metformin.
Metformin is NOT for you if you have severe kidney impairment, acute metabolic acidosis, or another contraindication identified by a clinician. The prescribing decision should account for kidney function, acute illness, alcohol intake, liver or heart conditions, and other medicines.
Digestive symptoms are the most common limitation. They often appear when treatment begins or when the dose increases.
Possible effects include:
These symptoms may lessen after the body adapts. Taking metformin with meals, increasing the dose gradually, and avoiding sudden dietary changes can help. Persistent diarrhoea deserves attention because dehydration can impair kidney function.
Lactic acidosis is rare but requires urgent medical assessment. Warning features can include severe weakness, unusual sleepiness, rapid or difficult breathing, persistent vomiting, abdominal pain, feeling cold, dizziness, or a slow or irregular heartbeat. The risk is higher with significant kidney impairment, severe illness, tissue hypoxia, heavy alcohol intake, or accumulation during dehydration.
Hypoglycaemia is uncommon with metformin alone. The risk becomes more relevant when metformin is combined with insulin, sulfonylureas, skipped meals, heavy exercise, or alcohol.
One detail patients often miss is that a normal glucose reading does not prove that every dose is being tolerated safely. Kidney function and hydration still matter. Another is that vitamin B12 deficiency may develop gradually, without the dramatic symptoms associated with low blood glucose.
Several everyday mistakes can reduce treatment benefit or increase risk:
A common misunderstanding concerns hypoglycaemia. Metformin alone rarely causes it, but the risk changes when insulin or an insulin-releasing medicine is added.
In clinical practice, physicians often describe metformin as a foundation rather than a complete diabetes strategy. It addresses insulin resistance and excess hepatic glucose production, but it does not replace nutrition planning, activity, kidney surveillance, or cardiovascular risk management.
A practical prescribing goal is gradual improvement without avoidable gastrointestinal distress. If a patient stops treatment after several days of nausea, the clinician may need to review meal timing, titration speed, kidney function, and the formulation before deciding that metformin cannot be tolerated.
Doctors also look beyond the glucose number. A suitable long-term plan considers HbA1c, eGFR, weight trend, blood pressure, lipid levels, B12 status, and symptoms of diabetes complications. Metformin can be a strong component of care, yet it has limits when beta-cell function has declined substantially or when kidney function changes.
Metformin is primarily used for Type 2 diabetes, not as a replacement for insulin in Type 1 diabetes. NICE guidance available in 2022 describes treatment pathways for Type 2 diabetes, while people with Type 1 diabetes require insulin because their bodies produce little or no usable insulin. In selected cases, a specialist may consider metformin as an additional treatment, but it does not replace insulin therapy .
Metformin begins affecting liver glucose production after treatment starts, but the measurable improvement in HbA1c develops over several weeks. The FDA prescribing information published in 2022 describes metformin as part of ongoing glucose management rather than a rapid rescue treatment. Daily readings may change before HbA1c reflects the full treatment response .
Metformin can be combined with insulin in Type 2 diabetes when the clinical plan requires both improved insulin sensitivity and direct insulin replacement. WHO guidance published in 2020 supports structured management of chronic noncommunicable diseases, including treatment adjustment as diabetes progresses. Insulin creates the main risk of hypoglycaemia in this combination, so glucose monitoring and dose review are important [3].
Some people experience modest weight reduction or remain weight-neutral during metformin treatment. The response varies with diet, physical activity, insulin resistance, diabetes duration, and other medicines. A 2022 NICE treatment pathway places weight management within wider diabetes care rather than treating metformin as a dedicated weight-loss medicine .
Long-term metformin use can reduce vitamin B12 absorption in some people. The risk may increase with longer treatment duration, higher exposure, or additional nutritional risk factors. FDA information and clinical guidance available in 2022 support checking B12 when symptoms such as anaemia, numbness, tingling, or unexplained fatigue develop .
Metformin dosing and suitability depend on eGFR because the kidneys remove the medicine from the body. Severe impairment, acute dehydration, or a sudden illness may require treatment interruption or a revised plan. The EMA’s diabetes-medicine guidance published in 2023 supports renal function assessment as part of safe antidiabetic treatment selection [4].
Your order will be securely packed and shipped within 24 hours. This is exactly what your package will look like (images of an actual item sent). It has the size and look of a regular private letter (24x11x0.7 cm) and its contents cannot be seen.


Metformin works best as part of a continuing Type 2 diabetes plan. Treatment decisions often include glycated haemoglobin testing, kidney function assessment, blood pressure management, lipid control, nutrition, physical activity, and screening for eye, kidney, nerve, and foot complications.
The first week brought loose stools after breakfast. Taking the tablet with a full meal helped, and the symptoms became occasional by the third week. My morning readings improved gradually rather than immediately.
I found the tablets easy to include with dinner. I did not lose much weight, but my appetite was slightly lower and my HbA1c improved at the follow-up appointment.
The nausea was difficult and I stopped for several days. The clinician restarted treatment more slowly, which was easier to tolerate. I needed more patience than I expected.
My glucose numbers improved, but I still needed changes to meals and walking. Metformin helped, though it was not enough by itself.
After years of treatment, tingling and tiredness led to a B12 check. The issue needed separate attention and was not explained by low glucose alone.
